Adequately informed consent was higher post- vs pre-bedside interpreter phone implementation (54% vs 29%) among LEP patients
Source
Lee (2017). Increased Access to Professional Interpreters in the Hospital Improves Informed Consent for Patients with Limited English Proficiency. Journal of General Internal Medicine.
Description #
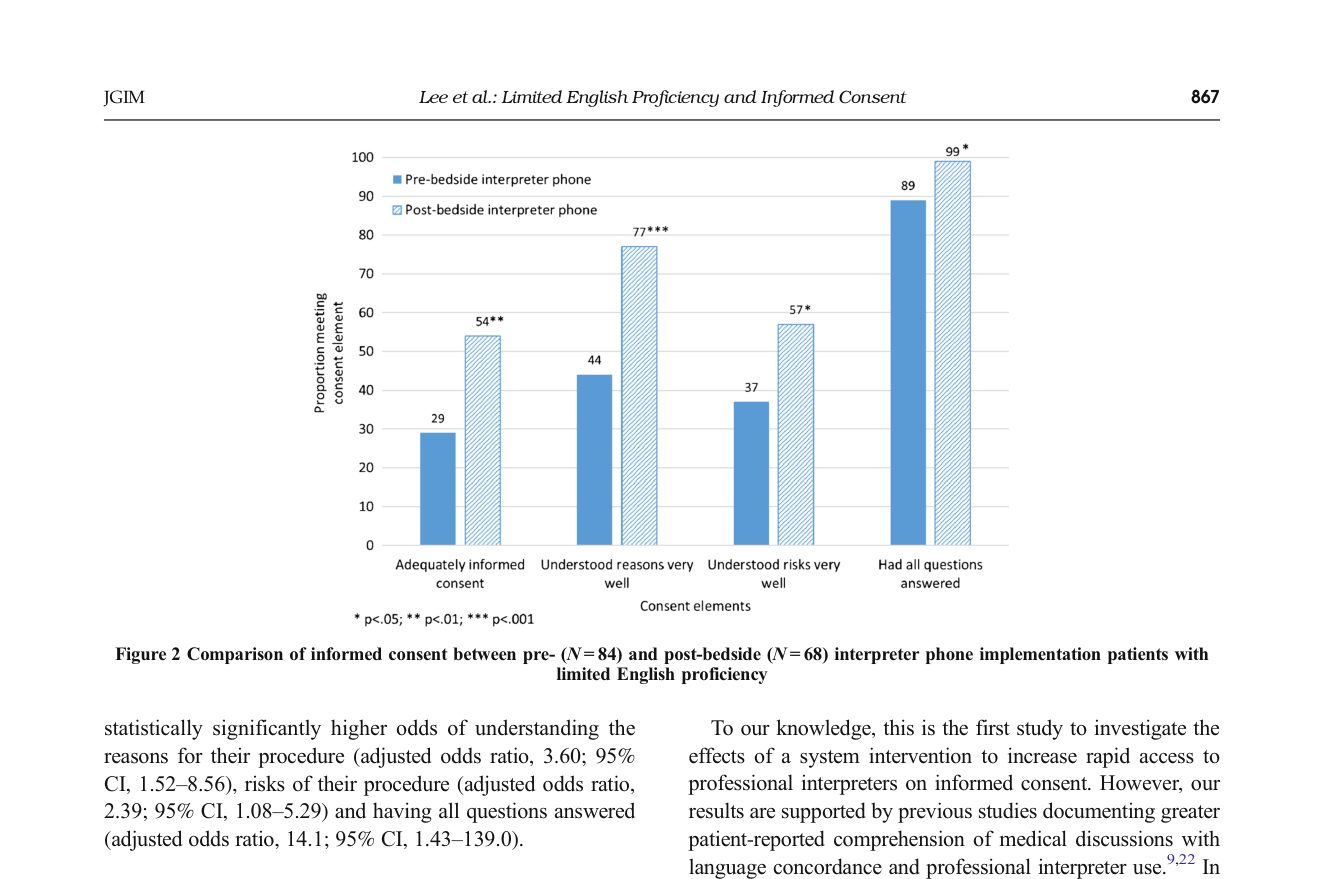
In this unadjusted pre-post comparison, the proportion of LEP patients meeting criteria for adequately informed consent (understanding the reasons and risks of the procedure "very well" and having had all questions answered) was significantly higher after the bedside interpreter phone intervention than before it: 54% post- vs. 29% pre-implementation (p = 0.001). The same significant post-implementation increase was present for each of the three individual consent elements (Fig. 2).
"As shown in Figure 2, the proportion of patients meeting criteria for adequately informed consent was significantly higher in the post-bedside interpreter phone implementation group compared to the pre-implementation group (post 54% vs. pre 29%, p = 0.001). This significant increase was present for each of the three individual informed consent elements." (Lee, 2017, p. 866)
Methods Context #
What? #ⓘ
The observable: a patient-centered, patient-reported measure of adequately informed consent — a binary composite of understanding the reasons and risks of the procedure "very well" and having had all questions answered.
"We considered consent to be adequately informed if the participant reported they understood the reasons and the risks very well and had all of their questions answered." (Lee, 2017, p. 865)
How? #ⓘ
A prospective pre-post natural-experiment design: identical structured interviews administered to LEP patients during the 6-month periods before and after a hospital-wide bedside interpreter phone rollout (A-0005ArtifactA-0005Initial AI draftBedside interpreter phone systemTo remove the time and availability barriers that keep clinicians from using professional interpreters in the hospital, by putting immediate, round-the-clock access to remote professional medical interpreters at every pa…); this cell reports the raw (unadjusted) pre-post proportions.
"This was a prospective, pre-post study, taking advantage of a natural experiment in which a large academic medical center implemented a hospital-wide intervention to increase rapid access to professional interpreters in the hospital." (Lee, 2017, p. 864)
Who? #ⓘ
152 Chinese- and Spanish-speaking hospitalized patients with LEP (84 pre- and 68 post-implementation), age ≥40, awaiting or having completed an invasive procedure on the cardiovascular, general surgery, or orthopedic surgery floors of one academic medical center; outcome data available for 151 (99%).
"We enrolled 152 Chinese- and Spanish-speaking patients with LEP (84 pre- and 68 post-implementation) and 86 English speakers." (Lee, 2017, p. 863)
Other Notes #
This is the unadjusted result; the propensity-score-adjusted estimate for the same composite outcome (AOR 2.56) is captured in a companion EVD.
Caveats #
- Small non-randomized pre-post observational design subject to confounding and secular trends The pre-post effect estimates come from a small, non-randomized observational study of a single academic medical center. Because assignment to the pre- vs. post-implementation groups was non-random, the data are subject to potential confounding; propensity-score adjustment can only account for measured confounders, not unmeasured ones. The authors also note that secular trends in informed consent discussions over the study period could have affected the results, though they report no other relevant interventions took place concurrently. Together these features mean the observed pre-post improvements in informed consent cannot be attributed to the intervention with certainty (the authors state causality cannot be proven).
- Outcomes rely on patient-reported comprehension and self-reported interpreter use, not objective measures The informed-consent outcomes are patient-reported comprehension — patient perception of whether they understood the reasons and risks and had their questions answered — rather than objective measures of knowledge, and the authors caution this perception may not correlate with objective knowledge (though they argue perception is itself a crucial, if imperfect, measure of whether consent was informed). Likewise, the study lacked objective measures of professional interpreter use during consent discussions and relied on patient self-report, so the interpreter-use estimates are vulnerable to recall and reporting error (compounded by missing interpreter-use data for a number of participants).