Children of LEP parents received fewer daily pain assessments than children of EP parents (7.3 vs 9.3 per day)
Source
Jimenez (2014). Postoperative pain management in children, parental English proficiency, and access to interpretation. Hospital Pediatrics.
Description #
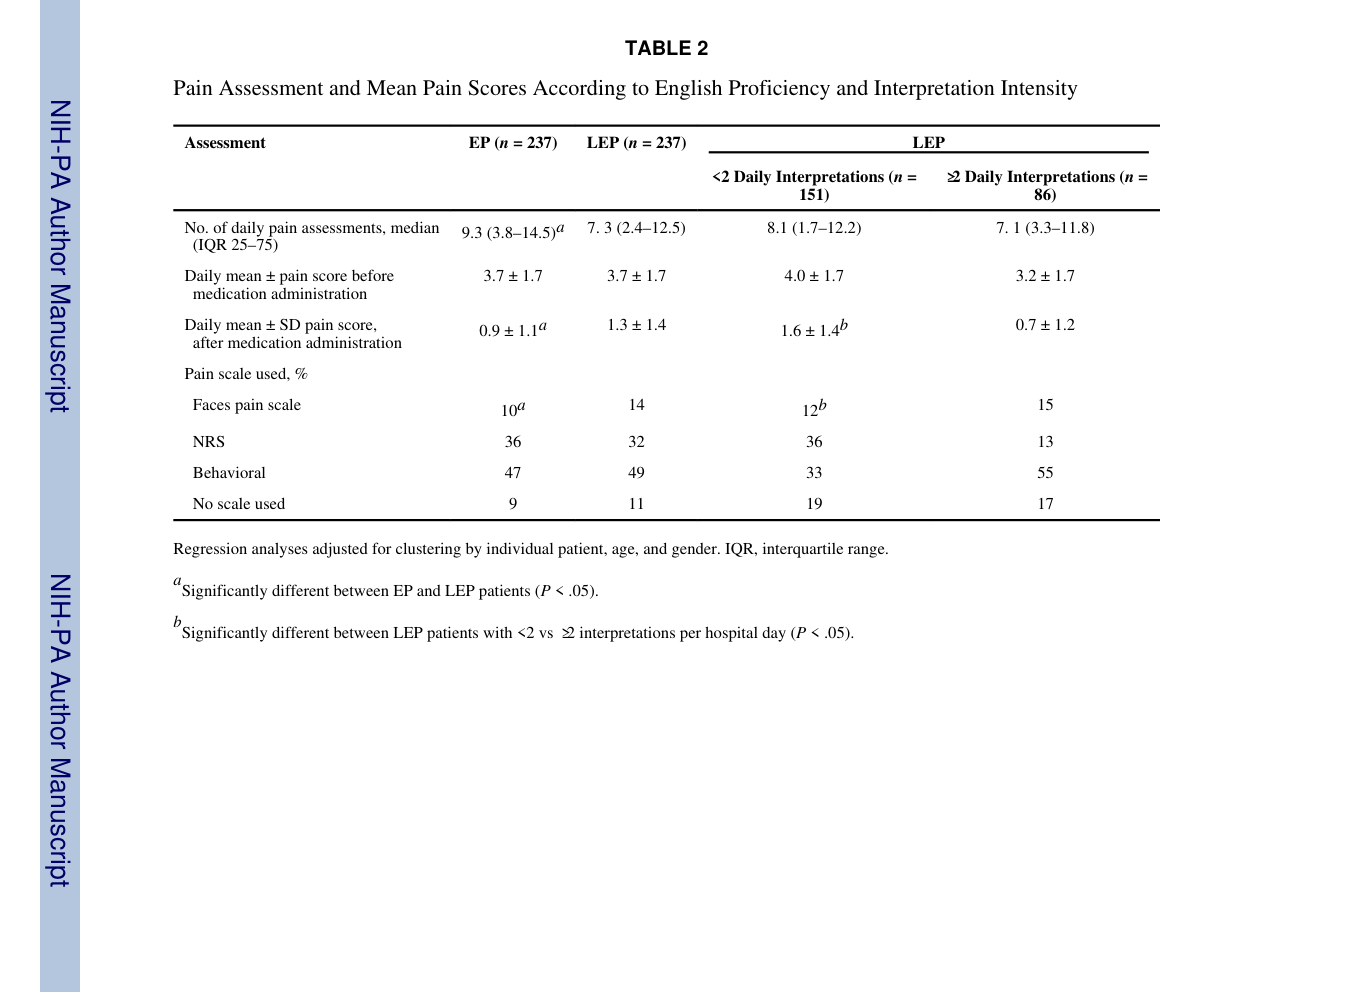 In this retrospective matched-cohort study of postsurgical children, the overall daily frequency of pain assessments (preanalgesic plus postanalgesic) was significantly lower for children of LEP parents than for children of English-proficient (EP) parents (7.3 [95% CI: 2.4–12.5] vs 9.3 [95% CI: 3.8–14.5]; P = .01). The two language groups did not differ significantly in preanalgesic mean daily pain scores, so the gap was in how often pain was assessed rather than in baseline pain level.
"The overall frequency of pain assessments (preanalgesic and postanalgesic administration) per day was lower for patients from LEP families compared with patients from EP families (7.3 [95% confidence interval: 2.4–12.5] vs 9.3 [95% confidence interval: 3.8–14.5], P = .01) (Table 2)." (Jimenez, 2014, p. 5)
"Children of LEP parents had fewer pain assessments (mean: 7 [95% confidence interval: 2–13] vs 9 [95% confidence interval: 4–15]; P = .012)" (Jimenez, 2014, p. 1)
Methods Context #
What? #ⓘ
The observable: the mean number of daily pain assessments recorded per child, obtained from the electronic medical record.
"Pain assessment and medication variables were as follows: (1) mean number of daily pain assessments; (2) mean daily pain scores before and after analgesic administration; and (3) type of analgesic given." (Jimenez, 2014, p. 3)
"Administration of pain medication triggered a mandatory documentation of pain assessment at the time of medication administration and 30 to 60 minutes after medication administration." (Jimenez, 2014, p. 3)
How? #ⓘ
Retrospective matched-cohort design: each LEP child was matched 1-to-1 to an EP child on age group, surgical procedure, and admission date, and the paired groups were compared with paired Wilcoxon signed rank tests.
"Children with LEP parents were matched 1-to-1 with children with EP parents, randomly chosen from a set of eligible subjects based on age category (<1, 1–3, 4–7, 8–12, and ≥13 years of age), type of surgery (based on International Classification of Diseases, Ninth Revision and Current Procedural Terminology codes), and admission date (within 1 month of index child admission date)." (Jimenez, 2014, p. 3)
"This retrospective matched cohort study evaluated the association between parental English proficiency, use of interpreter services, pain assessment, and analgesic treatment among pediatric surgical patients." (Jimenez, 2014, p. 2)
Who? #ⓘ
474 inpatient children aged 0–18 (237 LEP and 237 EP) admitted for surgery at a tertiary-care referral pediatric hospital (Seattle Children's Hospital) between January 1, 2008 and August 31, 2009.
"A total of 474 patients (237 with LEP parents and 237 with EP parents) were included in the study." (Jimenez, 2014, p. 5)
"Inpatient children 0 to 18 years of age admitted for a surgical procedure between January 1, 2008, and August 31, 2009, were eligible for the study." (Jimenez, 2014, p. 3)
Other Notes #
The abstract reports rounded values (7 vs 9; P = .012); the Results text and Table 2 give the precise medians (7.3 vs 9.3; P = .01). Both are quoted above.
Caveats #
- Findings come from a single tertiary pediatric hospital with a long-running program to expand interpreter access, limiting generalizability All data come from a single tertiary-care referral pediatric hospital (Seattle Children's Hospital) that had already invested in a multi-year institutional program to expand interpreter access, universal language-needs screening, and a twice-daily interpreted-care target. Both the observed LEP–EP disparities and the interpretation dose-response may differ at institutions with weaker interpreter infrastructure or different case mixes, so the single-center setting limits generalizability of the effect sizes.
- Retrospective design captured only pain assessments recorded at medication administration, so it cannot detect differences in the initiation of analgesia Because the study was retrospective and drew on documentation triggered by medication administration, it captured only the pain assessments that were recorded at the time analgesics were given (plus follow-up assessments). Assessments where a nurse evaluated a child but elected not to medicate were not captured. The authors therefore cannot determine whether the language groups differed in the initiation of medication — the counted assessment frequency and the opioid-timing distribution reflect medicated encounters, not all pain evaluations.