Communication board increased nurse satisfaction with the interpretation process (2.27 to 3.57, p=0.0007) in a pediatric surgery center
Source
Kiblinger (2022). Facilitating Communication in a Pediatric Surgery Center: Implementation of an Interactive Communication Board. Journal of Doctoral Nursing Practice.
Description #
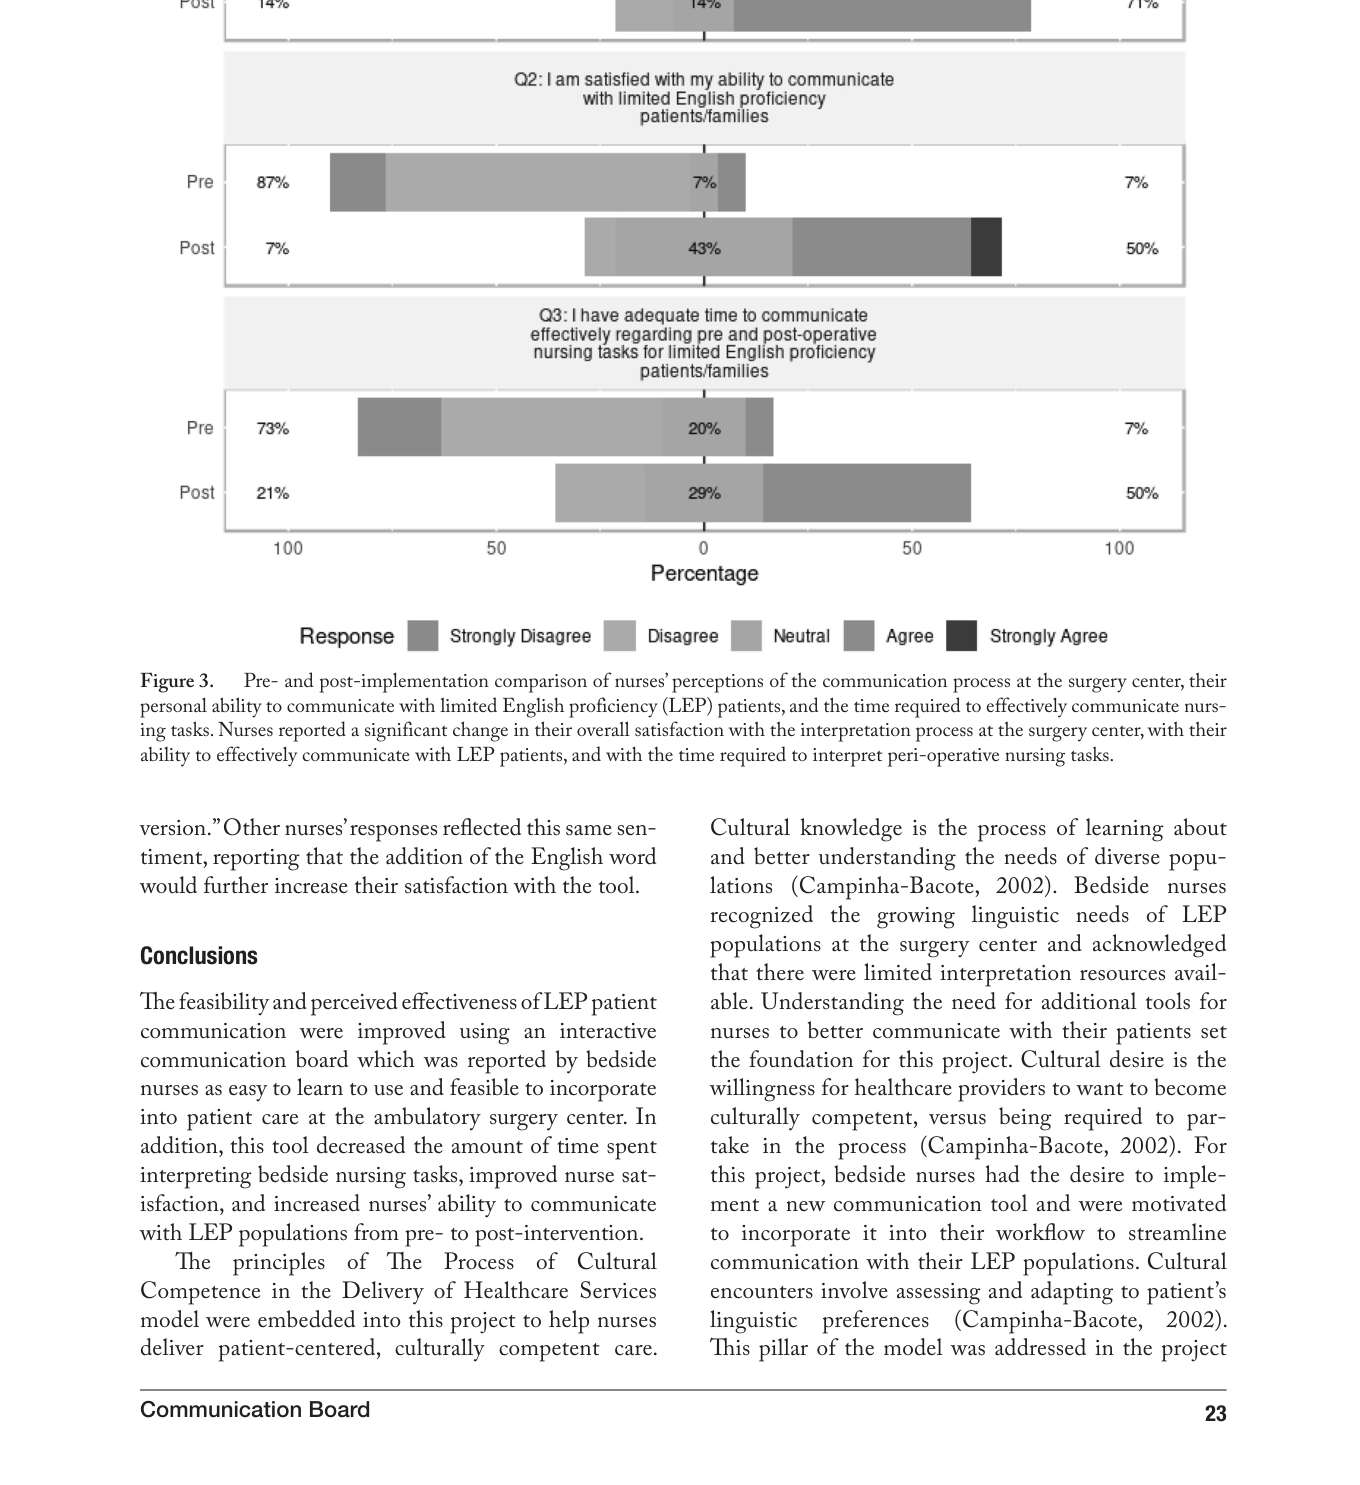
After a 3-month implementation of an interactive pictorial communication board, surgery-center nurses reported a 64% increase in satisfaction with the interpretation process, rising from a mean Likert rating of 2.27 (± 0.88) pre-intervention to 3.57 (± 0.76) post-intervention (p = 0.0007) on a 5-point scale (Figure 3). The change was statistically significant by Wilcoxon rank-sum test.
"Nurses reported a 64% increase in satisfaction with the interpretation process (2.27 ± 0.88 pre; 3.57 ± 0.76 post; p = 0.0007)." (Kiblinger, 2022, p. 22)
Methods Context #
What? #ⓘ
The observable: nurse-reported satisfaction with the process of interpreting/communicating with LEP patients, captured as a single 5-point Likert survey item.
"Sample pre-survey items included the following: (1) I am satisfied with the current process of communicating with LEP patients/families... Nurses responded using a standard 5-point Likert scale (1 = strongly disagree, 2 = disagree, 3 = neutral, 4 = agree, 5 = strongly agree)." (Kiblinger, 2022, p. 20)
How? #ⓘ
Single-group pre-post survey design evaluating the A-0014ArtifactA-0014Initial AI draftInteractive pictorial communication board (pediatric surgery center)An interactive pictorial communication board deployed in a pediatric ambulatory surgery center to let bedside nurses convey routine peri-operative nursing tasks to limited-English-proficiency (LEP) patients and caregiver…; paired pre- and post-implementation nurse responses compared with Wilcoxon rank-sum tests in R.
"A pre-post survey method was utilized to evaluate the implementation of the interactive communication board." (Kiblinger, 2022, p. 20)
"Wilcoxon rank-sum tests were performed to determine statistical significance between pre- and post-survey staff nurse responses." (Kiblinger, 2022, p. 22)
Who? #ⓘ
Staff nurses at a single large, urban pediatric ambulatory (three-OR) surgery center; surveys sent to all 17 nurses, with 15 completing the pre-survey (88%) and 14 the post-survey (82%).
"Surveys were distributed to all surgery center staff nurses (n = 17). Pre-surveys were completed by 88% of nurses (n = 15), and 82% of nurses completed the post-survey (n = 14)." (Kiblinger, 2022, p. 22)
Other Notes #
The Figure 3 bar chart plots this pre/post comparison alongside the perceived-ability and time-to-interpret measures.
Caveats #
- Uncontrolled pre-post design with concurrent bilingual-staff availability confounds attribution (Kiblinger board) The single-group pre-post design has no concurrent control arm, so improvements cannot be cleanly attributed to the board rather than to co-occurring factors. In particular, a bilingual staff member was available at the surgery center and was viewed by nurses as the most useful interpreting resource both before and after the intervention, providing an alternative explanation for perceived communication gains and for the low board utilization. [Inferred: the confounding/attribution weakness of the uncontrolled design is not stated by the authors as a formal limitation; the authors do note the bilingual-staff availability as a factor in the satisfaction–utilization contrast.]
- Small, homogenous, single-center nurse sample limits generalizability (Kiblinger board) The project drew on a very small, homogenous nurse sample (15 pre / 14 post of 17 nurses) at a single ambulatory surgery center within one large hospital system, so the effect estimates are imprecise and the findings may not transfer to other practice settings, patient populations, or non-surgical environments.
- Outcomes are nurse-perceived only with no LEP patient input or outcomes (Kiblinger board) The project measured only nurse-perceived communication outcomes; LEP patients and families were neither involved in developing the board nor assessed for their experience or for downstream clinical outcomes. The tool's actual effectiveness and readability from the patient/caregiver perspective therefore remain unknown, limiting claims about improved LEP communication to the provider's viewpoint.
- Self-reported outcomes vulnerable to social-desirability bias (Kiblinger board) All effectiveness outcomes are nurse self-reports on Likert surveys and are subject to social-desirability bias: nurses may have felt obligated to report improvement after the intervention. The authors themselves flag the striking contrast between the highly positive survey responses and the low actual board utilization as a signal that the satisfaction gains may be inflated.