Clinical risk-complexity and interpreter access ranked next-highest priority (RPN 2244, 2047)
Source
Maul (2012). Using a risk assessment approach to determine which factors influence whether partially bilingual physicians rely on their non-English language skills or call an interpreter. The Joint Commission Journal on Quality and Patient Safety.
Description #
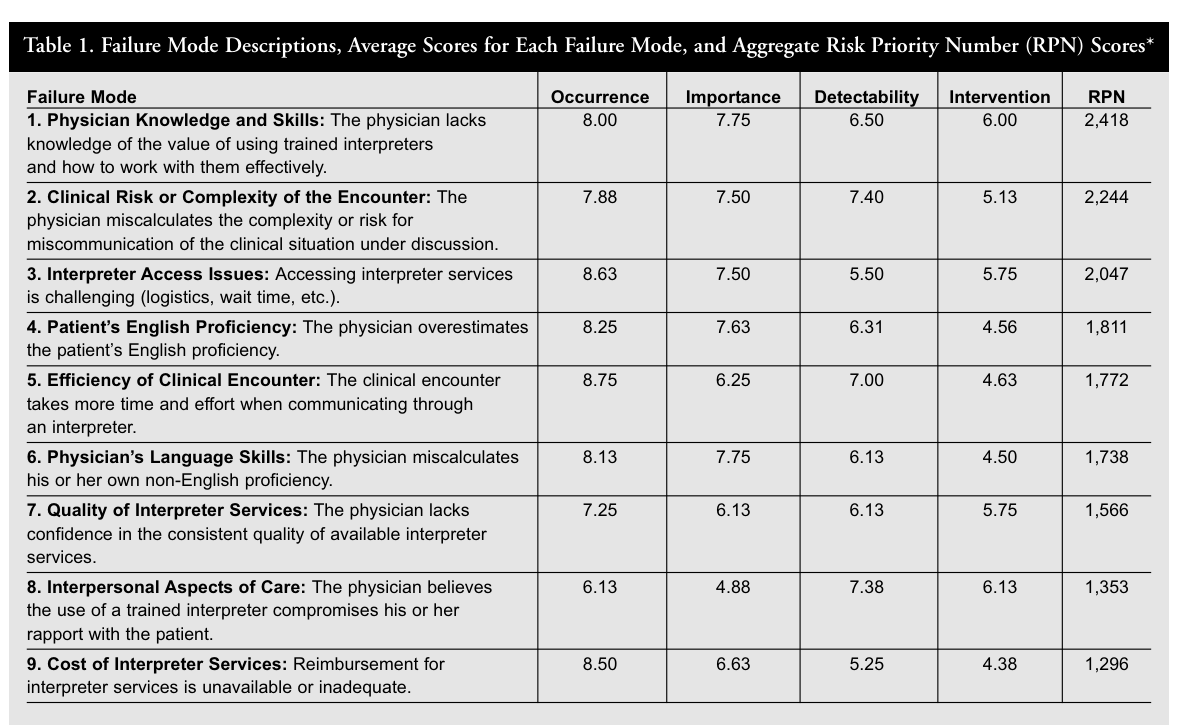
The two failure modes ranked immediately below the top factor were "Clinical Risk or Complexity of the Encounter" (the physician miscalculates the complexity or risk for miscommunication of the clinical situation) with an aggregate RPN of 2,244 (Occurrence 7.88, Importance 7.50, Detectability 7.40, Intervention 5.13), and "Interpreter Access Issues" (accessing interpreter services is challenging — logistics, wait time, etc.) with an aggregate RPN of 2,047 (Occurrence 8.63, Importance 7.50, Detectability 5.50, Intervention 5.75). The paper reports these two as ranking "closely behind" the top-scoring Physician Knowledge and Skills factor (Table 1).
"'Clinical risk or complexity of the encounter' and 'Interpreter access issues' had aggregate RPN scores that ranked closely behind." (Maul, 2012, p. 333)
Methods Context #
What? #ⓘ
The observable: the aggregate Risk Priority Number (RPN) for each failure mode, a composite of four expert-rated 1–10 scales.
"The purpose of generating an RPN score is to allow for a prioritization of policy-maker attention to individual failure modes on the basis of a composite of all four criteria." (Maul, 2012, p. 332)
How? #ⓘ
Panel members rated each failure mode on the four 1–10 scales; mean scores were multiplied to produce the aggregate RPN, and failure modes were then ordered by RPN to prioritize them (Table 1).
"When all major failure modes had been listed and clarified with concise definitions developed, HFMEA team members then scored each one according to four scales, providing ratings on the basis of past experience; data, if available; or the expert's intuition." (Maul, 2012, p. 331)
Who? #ⓘ
The national HFMEA expert panel of bilingual/partially bilingual physicians experienced in caring for LEP patients across multiple practice settings.
"Because we sought to explore an issue that might arise differently in a variety of institutional contexts, we chose experts from multiple types of practice settings (private practice and several types of institutional and group practices) with some variation in available interpreter services." (Maul, 2012, p. 330)
Other Notes #
These are two adjacent findings that the paper groups as the second-tier priorities ("ranked closely behind"); component scores read from Table 1 (page 333). RPNs are expert-derived prioritization scores, not measured harm rates (see qualifying caveats).
Caveats #
- Small rarified LEP-expert panel from well-resourced settings with possible social-desirability bias The ratings come from a small, non-representative panel and may be biased in ways that limit generalization of the rankings. The raters were a "rarified universe" of experts on LEP care — all highly experienced, most practicing in facilities with well-staffed interpreter services — so they may have underemphasized issues that matter more in less expert or less well-resourced settings; the authors specifically note the "cost" and "wait time" rankings might have differed had the raters been clinicians in smaller or rural practices. As focus-group–style elicitation, results could also reflect social desirability — panelists reporting what they perceived to be the "right answer" rather than their true views (e.g., cost possibly ranked low because members know laws mandate language services regardless of cost). Finally, the panel comprised only practicing physicians (a typical HFMEA uses a multidisciplinary team), and a few members were fully fluent rather than partially bilingual and had to reason from a hypothetical partially-bilingual standpoint. These features make the specific RPN ordering — especially for cost and access/wait-time factors — fragile and setting-dependent.
- Risk rankings are subjective expert-panel priority scores, not measured patient-safety outcomes The Risk Priority Numbers (RPNs) and their ordering are composite scores derived entirely from expert opinion — panel members rating each failure mode on four 1–10 scales "on the basis of past experience; data, if available; or the expert's intuition" — rather than measured rates of miscommunication or patient harm. HFMEA is a deliberately proactive method chosen precisely because most institutions have no observed record of severe harm from inappropriate use of physician language skills; the authors note that "with luck, no known poor outcomes are available within the organization to study." The RPN rankings therefore quantify perceived priority for intervention, not empirically observed effect sizes or risk magnitudes, and should not be read as measured probabilities of harm.