Patients needing language assistance reported lower average PACU pain (2.3 vs 2.6, p=0.046) after matching
Source
Kapoor (2023). The Impact of the Need for Language Assistance Services on the Use of Regional Anesthesia, Postoperative Pain Scores and Opioid Administration in Surgical Oncology Patients. J Pers Med.
Description #
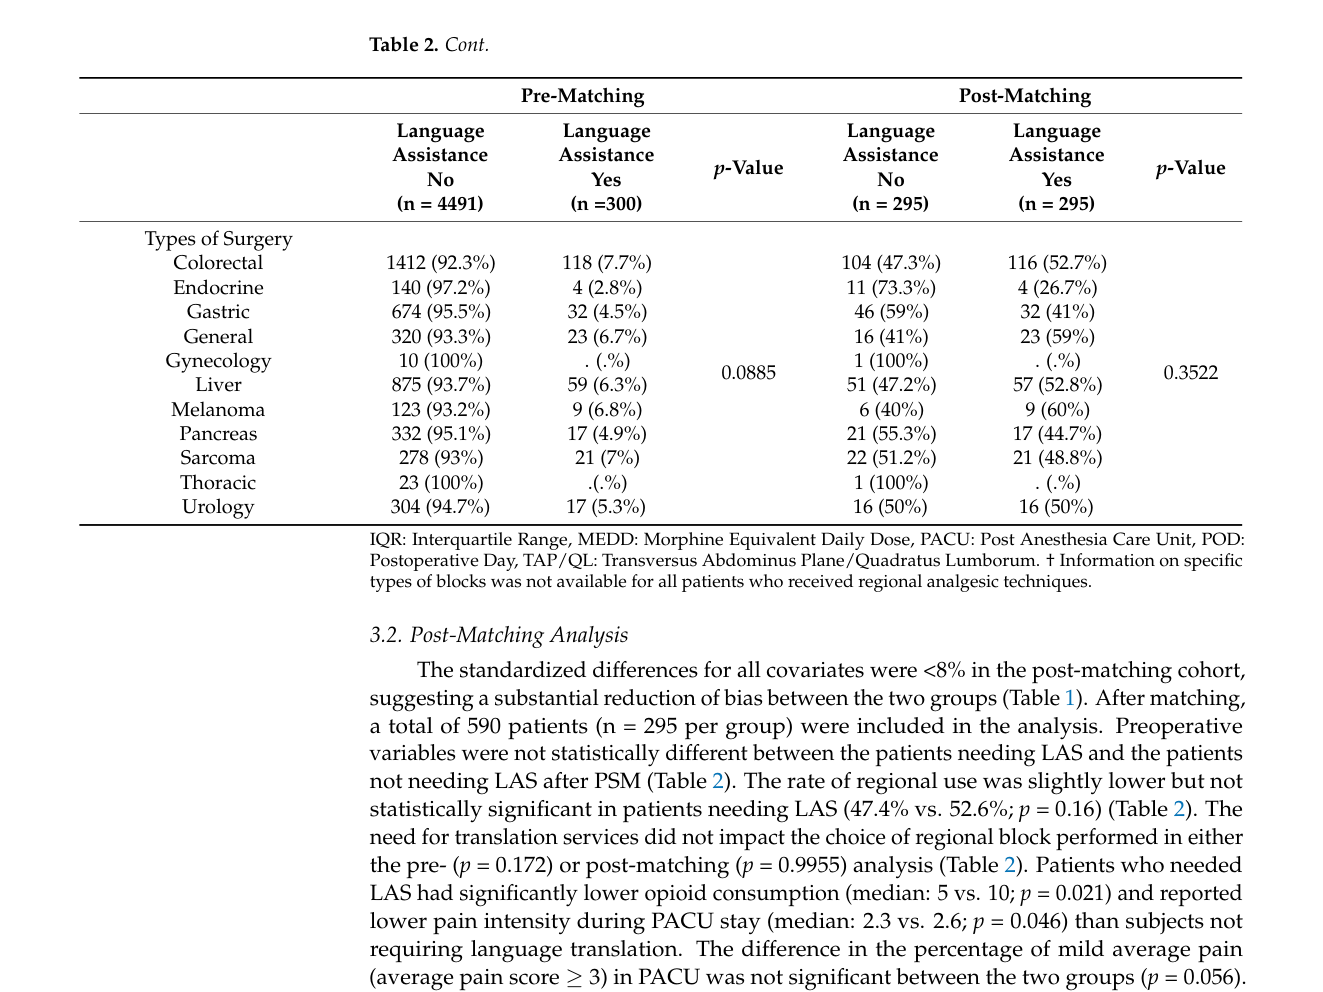
In the propensity-score-matched cohort (295 per group), patients who needed language assistance services (LAS) reported significantly lower average pain intensity during their PACU stay than patients who did not need LAS: median verbal numeric rating scale score 2.3 (IQR 1.0–3.5) vs 2.6 (IQR 1.3–3.8); p = 0.046 (Table 2). The authors emphasize the difference was statistically but not clinically significant (<1 unit on the 0–10 scale). This is the study's primary endpoint.
"Patients who needed LAS had significantly lower opioid consumption (median: 5 vs. 10; p = 0.021) and reported lower pain intensity during PACU stay (median: 2.3 vs. 2.6; p = 0.046) than subjects not requiring language translation." (Kapoor, 2023, p. 5)
Source inconsistency (flagged): the pre-matching Results prose states the opposite direction — "The latter [non-English-proficient patients] reported higher pain scores" — which contradicts both Table 2 (LAS-needing patients had lower median pain in every pre- and post-matching cell) and the post-matching prose quoted above.
"However, PACU's average and highest pain intensity statistically differed between English and non-English proficient patients (Table 2). The latter reported higher pain scores, although the difference was not clinically relevant (<1 unit on a scale 1/10)." (Kapoor, 2023, p. 4)
Methods Context #
What? #ⓘ
The observable: pain intensity, the primary endpoint, measured on a verbal numeric rating scale (0 = no pain, 10 = worst pain ever); here the average PACU pain score.
"The primary endpoint of the study was pain intensity (verbal numeric rating scale 0: no pain and 10: worst pain ever)." (Kapoor, 2023, p. 2)
How? #ⓘ
Retrospective cohort with propensity-score matching; continuous pain distributions compared between interpreter-needed vs not-needed groups using the Wilcoxon rank-sum test.
"Wilcoxon rank-sum test was used to compare location parameters of continuous distributions between patient groups." (Kapoor, 2023, p. 2)
Who? #ⓘ
The propensity-matched cohort of 590 adults (295 per group) undergoing open abdominal oncologic surgery at a single academic cancer center, 2016–2021.
"After matching, a total of 590 patients (n = 295 per group) were included in the analysis." (Kapoor, 2023, p. 5)
Other Notes #
Average PACU pain (post-matching, Table 2): LAS-No 2.6 (1.3–3.8) vs LAS-Yes 2.3 (1.0–3.5), p = 0.0460. Pre-matching: 2.7 vs 2.3, p < 0.0001 — same direction (LAS-needing lower).
Caveats #
- Statistically significant pain and opioid differences were likely not clinically significant The statistically significant differences in pain intensity (and the corresponding opioid difference) were very small — under 1 unit on the 0–10 scale — and, by the authors' own assessment, may not be clinically significant. A significant p-value here reflects the large sample rather than a meaningful clinical effect, so the lower pain scores in LAS-needing patients should not be over-interpreted as a clinically important benefit.
- Retrospective single-institution cancer-center study with residual confounding The study is retrospective and conducted at a single cancer center, so its estimates are vulnerable to residual confounding from unmeasured variables that could have influenced opioid-prescribing and pain outcomes, and its findings are tied to institution-specific practices (types of surgeries and regional anesthesia techniques). Although propensity-score matching reduced measured baseline imbalance, no prior sample-size analysis was performed and unknown confounders remain. This limits causal interpretation and external generalizability of the pain, opioid, and regional-anesthesia associations.
- Cultural differences in numeric pain-scale psychometrics could bias reported scores Pain was measured with a numeric verbal rating scale whose interpretation may vary across languages and cultures. Cultural differences in how patients understand and report numbers on the scale could have systematically biased the reported pain scores between the LAS-needing and English-proficient groups, threatening measurement equivalence and thus the validity of the between-group pain comparisons.
- Actual mode and use of interpreters could not be determined; LAS need is a proxy The exposure is the need for language assistance services (recorded when a patient asked for an interpreter at their first encounter), not verified interpreter utilization. The actual use and mode of interpretation — phone, videoconferencing, or in-person — could not be retrospectively determined. Because interpreter modality and whether an interpreter was actually deployed at the point of pain assessment are unknown, the observed pain and opioid differences cannot be attributed to any specific form or dose of language assistance.