Need for language assistance was not associated with regional anesthesia use after matching (47.4% vs 52.6%, p=0.16)
Source
Kapoor (2023). The Impact of the Need for Language Assistance Services on the Use of Regional Anesthesia, Postoperative Pain Scores and Opioid Administration in Surgical Oncology Patients. J Pers Med.
Description #
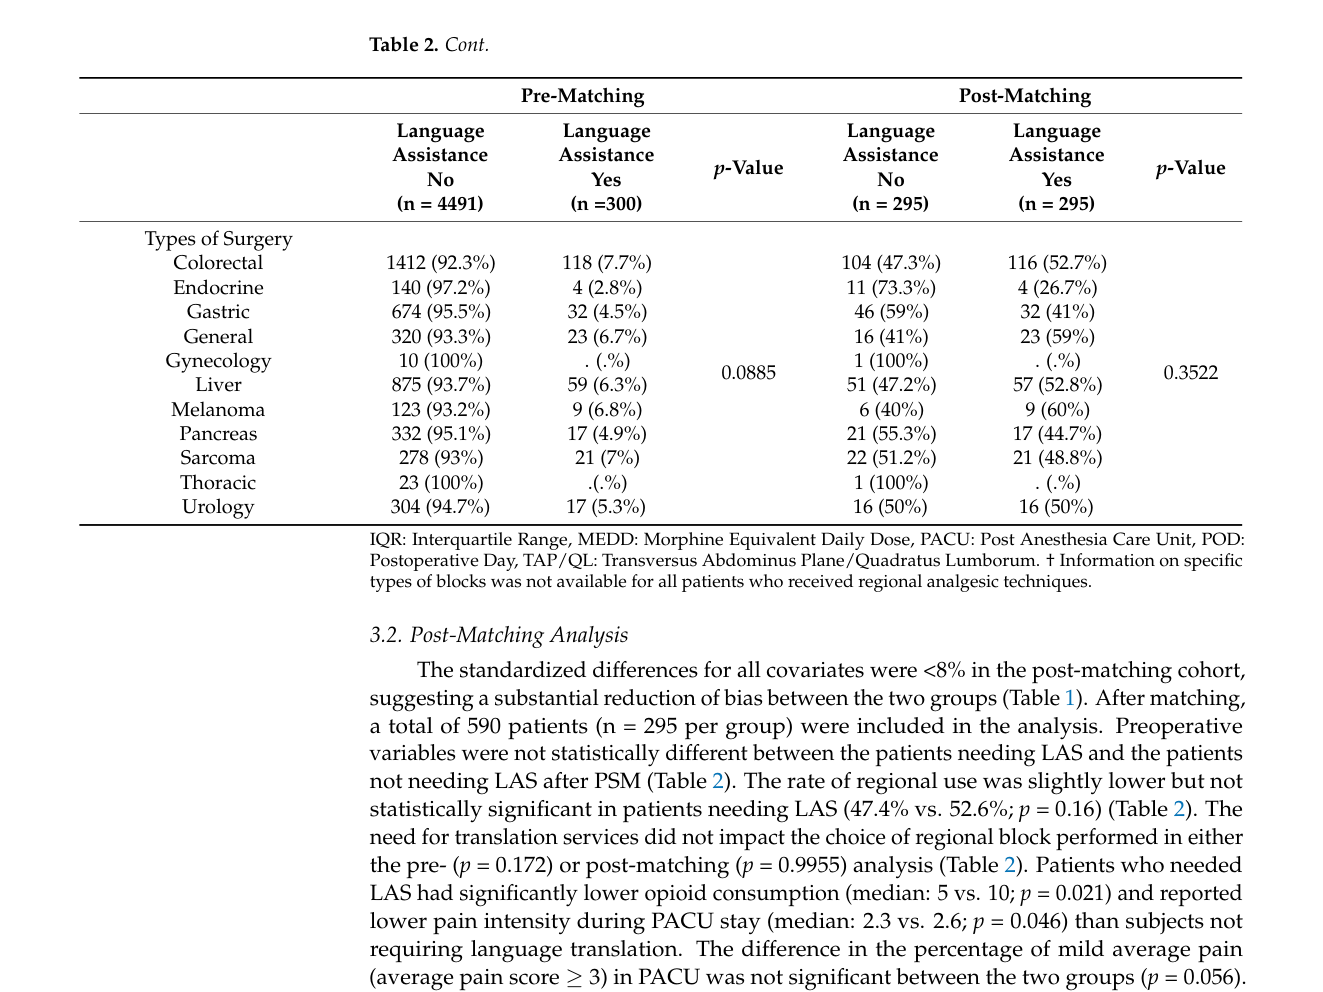
In the propensity-score-matched cohort (295 per group), the rate of regional anesthesia use was slightly lower among patients who needed language assistance services (LAS) than among those who did not (47.4% vs 52.6%), but this difference was not statistically significant (p = 0.16). The choice of regional block type (epidural vs TAP/QL) also did not differ by LAS need (post-matching p = 0.9955). This is a null result: need for LAS was not associated with regional anesthesia utilization after matching (Table 2).
"The rate of regional use was slightly lower but not statistically significant in patients needing LAS (47.4% vs. 52.6%; p = 0.16) (Table 2)." (Kapoor, 2023, p. 5)
"The need for translation services did not impact the choice of regional block performed in either the pre- (p = 0.172) or post-matching (p = 0.9955) analysis (Table 2)." (Kapoor, 2023, p. 5)
Methods Context #
What? #ⓘ
The observable: whether the patient received regional anesthesia/analgesia (and the type of regional block), a secondary endpoint.
"Secondary endpoints included opioid use in PACU and the use of regional analgesia." (Kapoor, 2023, p. 2)
How? #ⓘ
Retrospective cohort with propensity-score matching (Greedy 5→1 digit algorithm) comparing patients needing vs not needing an interpreter; the categorical association was tested with chi-square / Fisher's exact test.
"The Greedy 5 -> 1 digit match algorithm was used to match the baseline covariates so that the two groups (no interpreter needed vs. interpreter needed) would have similar propensity scores." (Kapoor, 2023, p. 2)
Who? #ⓘ
The propensity-matched cohort of 590 adults (295 per group) undergoing open abdominal oncologic surgery at a single academic cancer center (MD Anderson), 2016–2021.
"After matching, a total of 590 patients (n = 295 per group) were included in the analysis." (Kapoor, 2023, p. 5)
Other Notes #
Regional anesthesia row (post-matching, Table 2): received regional — LAS-No 169 (52.6%) vs LAS-Yes 152 (47.4%). The authors interpret the (non-significant) lower rate as LAS possibly aiding patients' decision to accept regional anesthesia.
Caveats #
- Retrospective single-institution cancer-center study with residual confounding The study is retrospective and conducted at a single cancer center, so its estimates are vulnerable to residual confounding from unmeasured variables that could have influenced opioid-prescribing and pain outcomes, and its findings are tied to institution-specific practices (types of surgeries and regional anesthesia techniques). Although propensity-score matching reduced measured baseline imbalance, no prior sample-size analysis was performed and unknown confounders remain. This limits causal interpretation and external generalizability of the pain, opioid, and regional-anesthesia associations.
- Actual mode and use of interpreters could not be determined; LAS need is a proxy The exposure is the need for language assistance services (recorded when a patient asked for an interpreter at their first encounter), not verified interpreter utilization. The actual use and mode of interpretation — phone, videoconferencing, or in-person — could not be retrospectively determined. Because interpreter modality and whether an interpreter was actually deployed at the point of pain assessment are unknown, the observed pain and opioid differences cannot be attributed to any specific form or dose of language assistance.