Unadjusted median peri-operative LOS fell monotonically from 11 to 1 day across ascending interpreting-frequency quartiles
Source
Claire de Crescenzo (2022). Increasing Frequency of Interpreting Services is Associated With Shorter Peri-operative Length of Stay. Journal of Surgical Research.
Description #
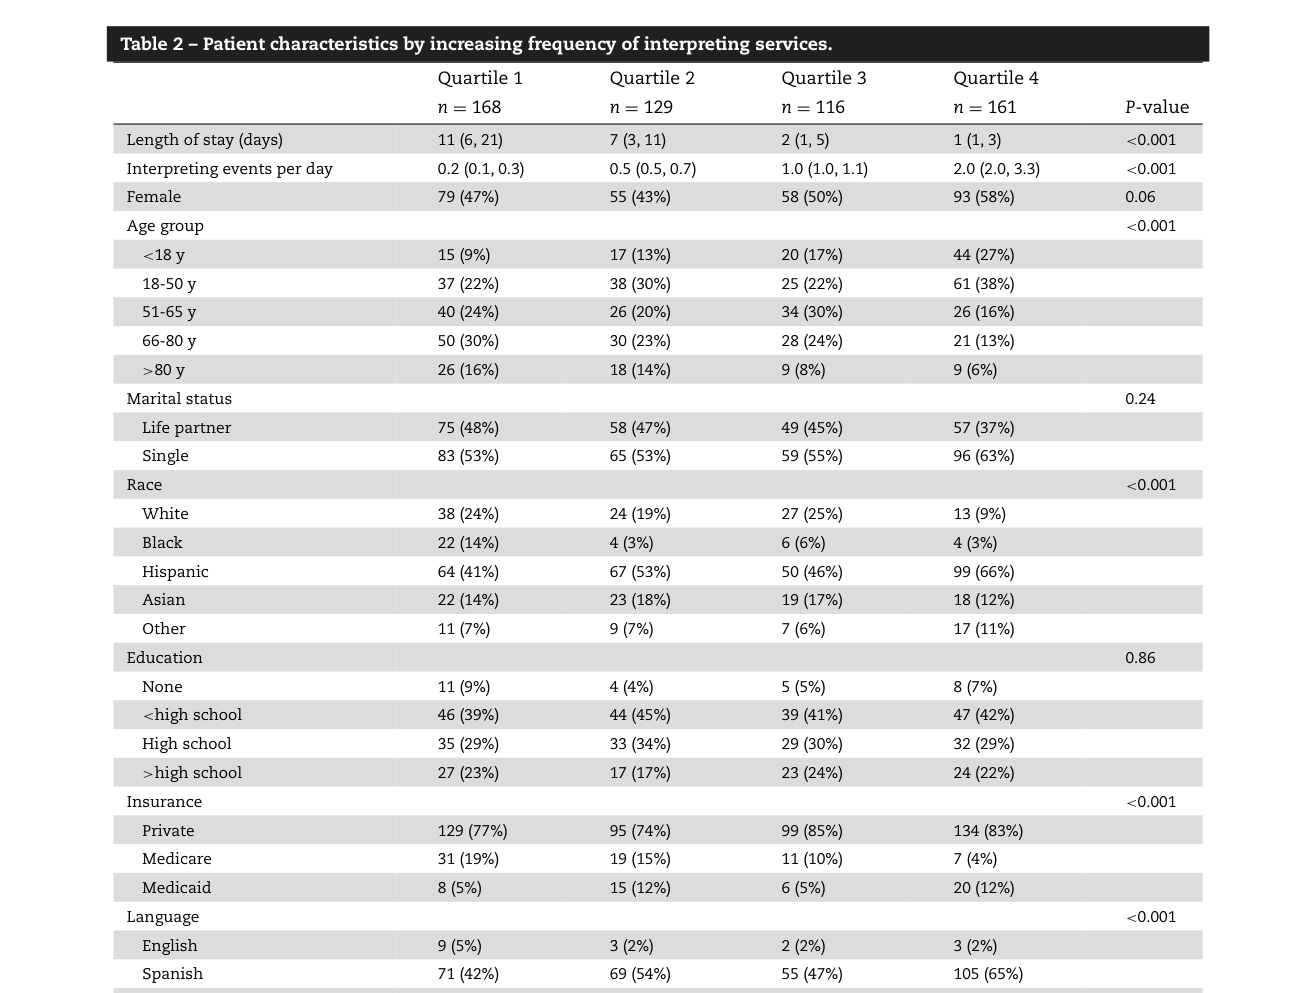
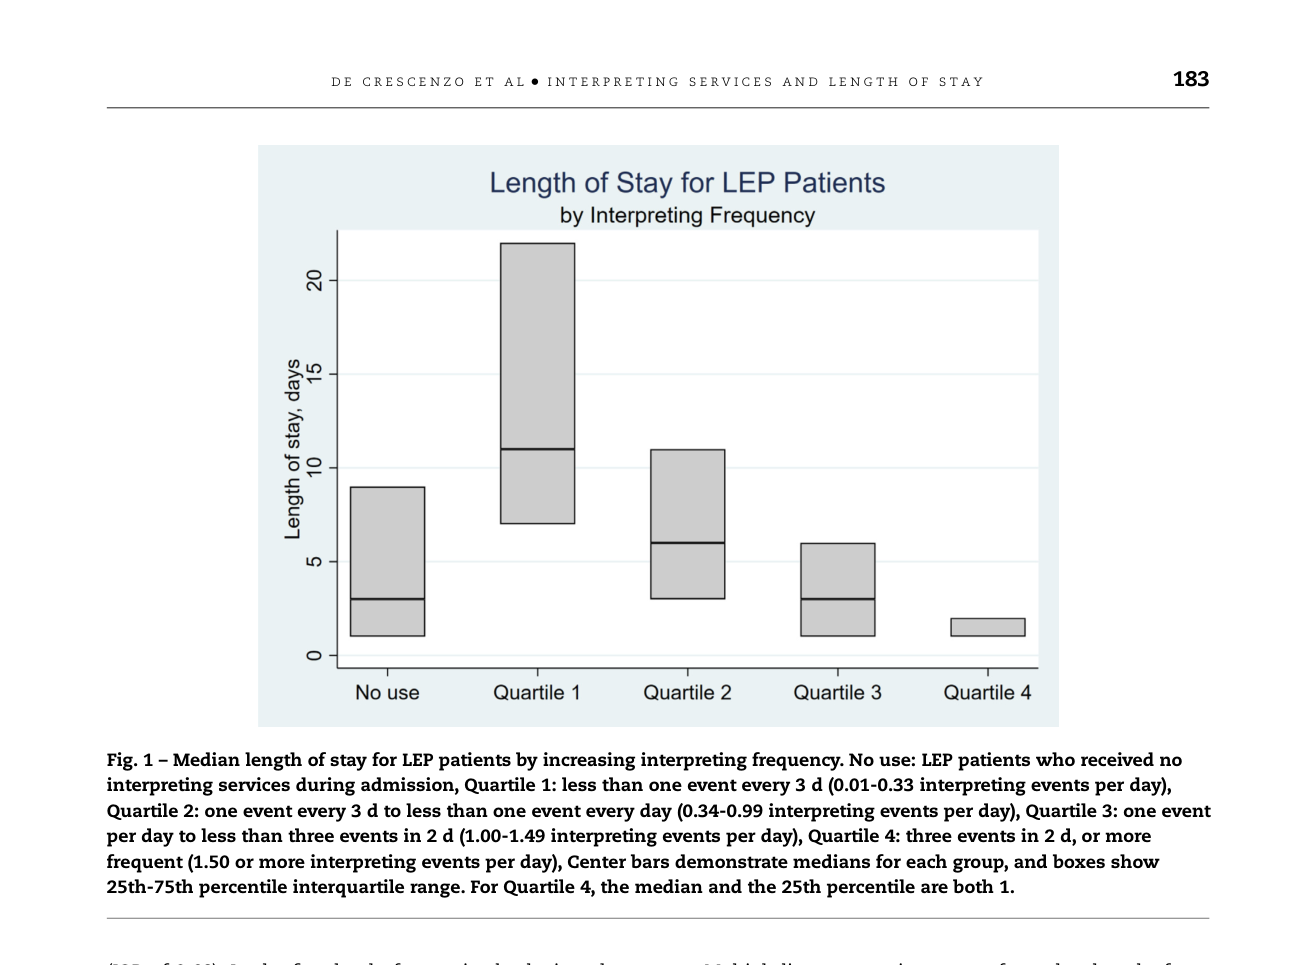
On unadjusted analysis, median peri-operative length of stay decreased monotonically across the four ascending quartiles of interpreting-event frequency, falling from 11 days (IQR 6, 21) in the lowest-frequency quartile 1 to 2 days in quartile 3 and 1 day (IQR 1, 3) in the highest-frequency quartile 4, a difference significant at P < 0.001 (Table 2, Fig. 1). This is the raw (unadjusted) exposure-response gradient later tested with covariate adjustment.
"On unadjusted analysis of length of stay among quartiles of increasing frequency of interpreting events admissions, median length of stay decreased with increasing number of interpreting events per day, dropping from 11 d (IQR 6, 21) in quartile 1 (lowest frequency InEpD) to 1 d (IQR 1, 3) in quartile 4 (highest frequency InEpD) (Table 2, Fig. 1)." (de Crescenzo, 2022, p. 183)
"Length of stay (days) 11 (6, 21) 7 (3, 11) 2 (1, 5) 1 (1, 3) <0.001" (de Crescenzo, 2022, p. 181, Table 2)
Methods Context #
What? #ⓘ
The observable: peri-operative length of stay in days, compared across quartiles of interpreting-event frequency (the exposure).
"The primary outcome was length of stay in days and the independent variable of interest was frequency of interpreting, measured in interpreting events per day." (de Crescenzo, 2022, p. 179)
How? #ⓘ
Unadjusted comparison of median LOS across four approximate quartiles of ascending interpreting-event frequency (Kruskal-Wallis for the continuous outcome), in a cross-sectional study of 2018 peri-operative admissions.
"The admissions were divided into four approximate quartiles of increasing frequency of interpreting events during admission." (de Crescenzo, 2022, p. 179)
Who? #ⓘ
545 patients across 574 peri-operative admissions of at least one night during 2018 who used medical interpreting services at a tertiary academic medical center in the Boston metro area.
"A total of 545 patients used interpreting services at least once during 574 peri-operative admissions." (de Crescenzo, 2022, p. 180)
Other Notes #
Quartile bins: Q1 = 0.01–0.33 interpreting events/day (< once every 3 d); Q4 = 1.50 or more events/day. The intermediate quartile medians were 7 d (Q2) and 2 d (Q3).
Caveats #
- Cross-sectional design cannot establish causality and interpreting-events-per-day has LOS in its denominator (Claire 2022) The study is cross-sectional and, as the authors state, was not designed to demonstrate causality; the association between higher interpreting frequency and shorter LOS could reflect reverse or confounded pathways rather than an effect of interpreting. A specific structural concern reinforces this: the exposure is interpreting events per day, i.e. total interpreting events divided by length of stay, so length of stay is in the denominator of the exposure. Mechanically, a short admission (few days) tends to yield a higher events-per-day value for the same or fewer total encounters, which can manufacture an inverse exposure-outcome association independent of any causal benefit. The authors frame the finding as motivating an interventional study rather than as evidence of a causal effect.
- Small single-institution study of heterogeneous operations with incomplete operative-complexity adjustment (Claire 2022) This is a small, single-institution study whose patients underwent a heterogeneous array of operations of varying complexity, and operative complexity is a strong determinant of length of stay. The complexity-correction factors used (CPT groupings and RVU quartiles) do not exhaustively capture those differences, leaving residual confounding by case mix as a plausible partial explanation for the shorter LOS at higher interpreting frequencies. The single-center, single-year setting also limits generalizability, since medical interpreting services are not standardized and vary substantially across institutions and geographic locations. The authors ran a five-model sensitivity analysis as a partial mitigation but acknowledge it does not fully correct for complexity.
- Language-concordant staff and non-spoken communication gaps were not captured, misclassifying true communication frequency (Claire 2022) The exposure (interpreting events per day from the interpreting office) undercounts actual language-concordant communication: encounters where a language-concordant provider communicated directly with an LEP patient without engaging an interpreter are not recorded in the data, so some patients coded as low-frequency may in fact have had adequate communication. The measure also captures only spoken-language interpreting and does not account for other patient-provider communication gaps such as reading and health literacy or the navigability of written discharge and follow-up materials. Both forms of misclassification blur the mapping between the recorded interpreting frequency and the true adequacy of communication that the LOS association is meant to reflect.