LEP status was not associated with postoperative complication rates (21.93% vs 23.36%, P>0.05) after breast reduction
Source
Wang Fei (2024). Limited English Proficiency Is Not Associated With Poor Postoperative Outcomes or Follow-Up Rates in Patients Undergoing Breast Reduction Mammoplasty – A Single Institution Retrospective Cohort Study. Journal of Surgical Research.
Description #
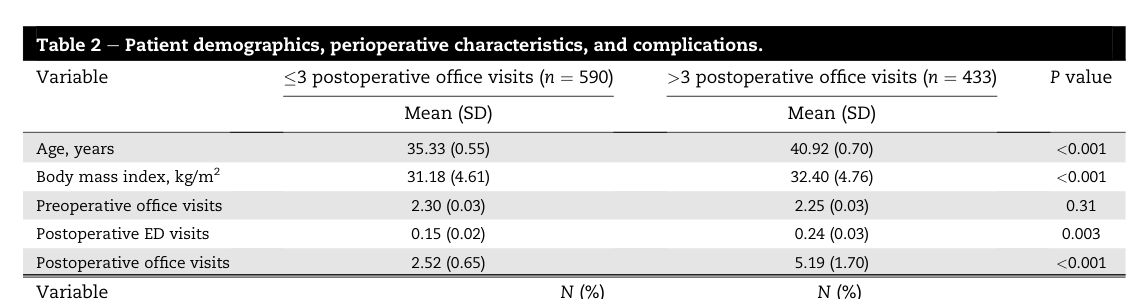
On bivariate testing there was no significant difference in the rate of any postoperative complication between limited-English-proficiency (LEP) and non-LEP patients after primary bilateral breast reduction mammoplasty: 21.93% of non-LEP patients versus 23.36% of LEP patients experienced any complication (P > 0.05). This is a null result — the LEP rate was numerically slightly higher but not statistically distinguishable — and it opposes the claim that LEP worsens postoperative complication rates. The comparison is reported in the Results text; Table 2 breaks complications down by follow-up cohort rather than by LEP status, so the exact LEP-vs-complication cross-tabulation is text-only.
"There were no significant differences between complication rates and LEP status on bivariate testing, with 21.93% of non-LEP patients experiencing any complications versus 23.36% of LEP patients (P > 0.05)." (Fei, 2024, p. 691)
Methods Context #
What? #ⓘ
The observable: presence of any postoperative complication within 3 months, collated as the binary composite "any complication."
"All complications were collated to form the composite 'any complication' in which 'yes' would indicate the presence of any aforementioned complications." (Fei, 2024, p. 690)
How? #ⓘ
Unadjusted between-group (bivariate) comparison of categorical rates using Chi-square analysis with Fisher's exact test.
"Student's t-test, Kruskal–Wallis U-test, and Chi-square analysis with Fisher's exact test were used to perform between cohort comparisons of patient characteristics, comorbidities, perioperative and postoperative statistics." (Fei, 2024, p. 691)
Who? #ⓘ
1023 women aged ≥18 undergoing primary bilateral breast reduction mammoplasty at a single urban academic center (2015–2019); 21% were LEP (all of whom used interpreters).
"Patients were eligible and included in the study if they were women 18 y or older undergoing primary bilateral BRM without any adjunct procedures." (Fei, 2024, p. 690)
Other Notes #
The composite complications were most often T-point dehiscence (10.37%), wound healing (7.73%), and infection (5.97%). The exposure "LEP status" was proxied by documented interpreter use / non-English consent forms (see qualifying caveat on the interpreter-use proxy). Table 1's LEP counts (No 807 + Yes 241 = 1048) exceed the analytic N = 1023, a minor internal inconsistency in the demographics table.
Caveats #
- LEP status was proxied by documented interpreter use and non-English consent forms, not directly measured (Wang 2024) The exposure of interest, LEP status, was never measured directly. It was operationalized as a proxy — patients who had documented interpreter use and/or required non-English consent forms in the chart were classified as LEP. Because all LEP patients in the cohort used interpreters, the study cannot separate the effect of language discordance from the effect of receiving interpreting services, and any LEP patients who did not have interpreter use or non-English consent documented would be misclassified as non-LEP. [Inferred: non-differential misclassification of the exposure of this kind tends to bias effect estimates toward the null, so the reported null associations may partly reflect exposure measurement error rather than a true absence of effect.]
- Retrospective single-center BRM cohort, predominantly Spanish-speaking and possibly underpowered to detect a small LEP association (Wang 2024) The null LEP associations come from a retrospective, observational, single-institution cohort — not a randomized trial — so measured and unmeasured confounders could not be fully controlled despite multivariable adjustment. The authors explicitly note the sample may be inadequate to detect a small but genuine LEP effect, which is the central threat to interpreting these nulls as true absence of effect. The cohort was also predominantly Spanish-speaking, precluding stratification by language, and drawn from a single urban academic center with an LEP rate nearly double the U.S. average, limiting generalizability (especially to rural settings and non-Spanish LEP groups). Together these features make the null findings hypothesis-consistent but not confirmatory of "no effect."